Facial jowls
back to main page
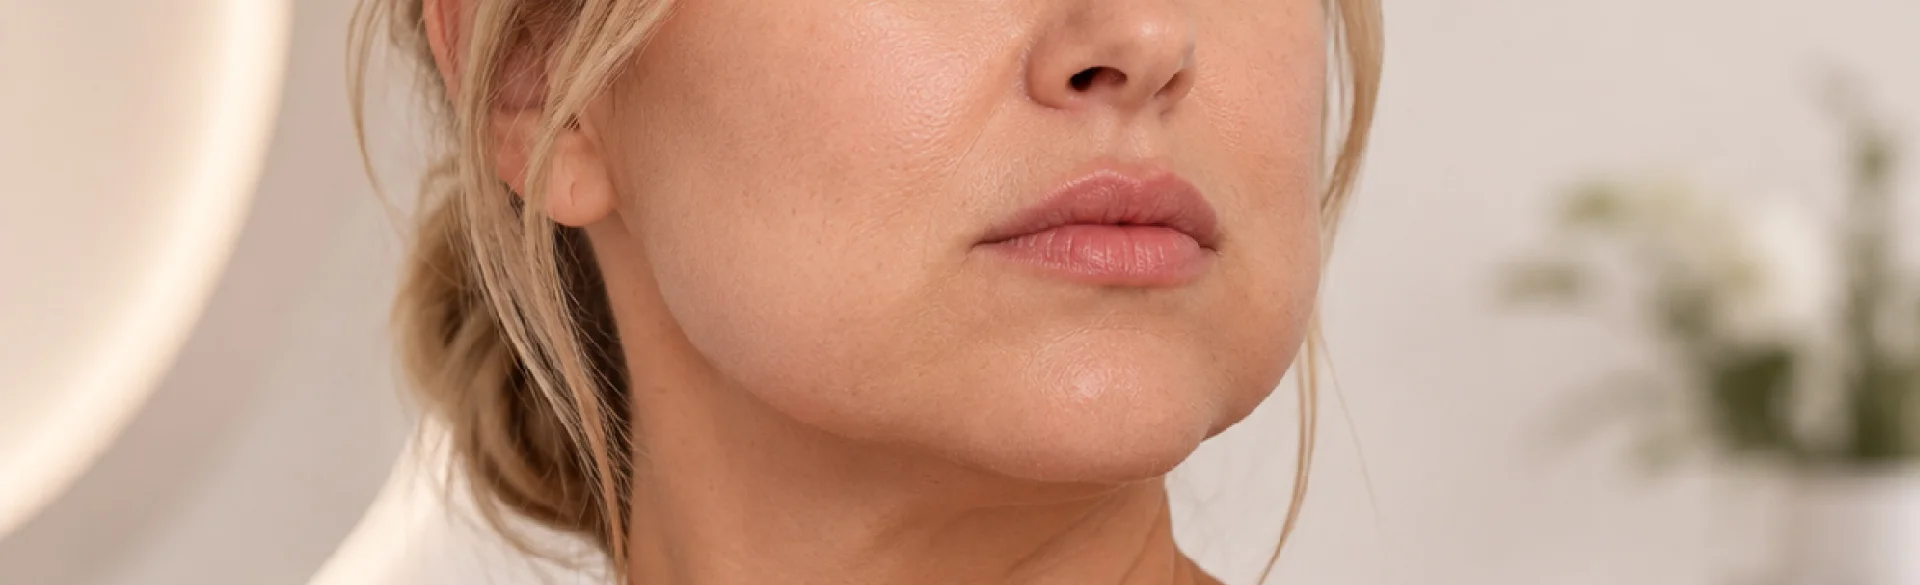
"Hamsters" on the face is a colloquial term for sagging tissues visible on both sides of the lower part of the face, around the jawline. In English-language literature, they correspond to the term jowls or jowl deformity. They are not a disease, but a change in facial contour resulting from the interaction of multiple processes: loss of skin elasticity, subcutaneous tissue remodeling, weakening of supporting structures, myofascial changes, and gradual remodeling of the craniofacial bones. Jowls can appear even in young people with a specific anatomical structure, but they most often become visible with age. The method of their correction should result from the cause of the problem, as excess adipose tissue, skin laxity, and the sagging of deeper tissues require different approaches.
Facial jowls - what are they
Jowls are a localized disruption of the smooth contour of the jawline. They usually form laterally to the labiomandibular fold, also known as the marionette line, and can partially extend beyond the lower border of the mandible. From an anatomical point of view, they are not merely „excess fat”. They are formed in varying proportions by:
- lax skin and subcutaneous connective tissue,
- superficial fat compartments of the lower face,
- displaced cheek tissues,
- elements of the musculoaponeurotic system, including the platysma muscle,
- differences in the bony support of the mandible and chin.
An important role is played by the region of the mandibular ligament and the attachments of the muscles depressing the lower lip and the angle of the mouth. The tissues located anterior to this area are relatively more firmly anchored to the underlying base, whereas the subcutaneous tissue located further laterally must maintain high mobility during mouth opening. With aging, the fibrous connections between the skin and deeper layers elongate and lose some of their mechanical properties. This results in local redundancy—an excess and folding of tissues characteristic of jowls.
This term should not be equated with a double chin. Jowls are located primarily on the sides of the anterior part of the mandible, whereas a double chin involves the submental area. However, both problems can coexist.
Jowls on the face - what do they look like
The most typical symptom is the loss of a straight, defined jawline. A bulge appears in the lower part of the cheek, which may be visible only in specific lighting or form a distinct fold extending beyond the mandibular border. The change is usually bilateral, but does not have to be perfectly symmetrical.
Characteristic features include:
- widening of the lower third of the face,
- a change in the facial contour from triangular or oval to more rectangular,
- interruption of the smooth line between the chin and the angle of the mandible,
- deepening of the labiomandibular folds,
- optical downturning of the corners of the mouth,
- coexisting laxity of the cheeks, chin, or neck.
The appearance of jowls depends on the dominant mechanism. With thin, lax skin, they take the form of a soft fold. With a larger amount of adipose tissue, they are fuller and heavier. If the underlying issue is weak bony support, especially a small or recessed chin, even moderate tissue sagging can significantly disrupt the profile.
Pre-treatment assessment should include the face at rest and in motion, in anterior, lateral, and oblique views. The physician analyzes skin quality, fat distribution, chin and mandible proportions, platysma muscle function, and the degree of midface sagging. This makes it possible to distinguish true jowls from bulky masseter muscles, swelling, salivary gland disorders, or isolated submental fat accumulation.
Jowls on the face - why do they appear
The formation of jowls is a multilayered process. It cannot be explained solely by the effects of gravity. Skin, adipose tissue, ligaments, fasciae, muscles, and the facial skeleton all age simultaneously.
The most important mechanisms include:
- Skin aging. The amount of collagen, elastin, and glycosaminoglycans decreases, and their organization changes. The skin becomes thinner, less elastic, and less resistant to tissue displacement.
- Remodeling of fat compartments. Facial adipose tissue is divided into distinct superficial and deep compartments. They do not age uniformly. Some lose volume, while others shift or become more prominent. Atrophy of the supporting cheek compartments can indirectly increase the load on the lower part of the face.
- Changes in fibrous attachments and the SMAS system. The SMAS, or superficial musculoaponeurotic system, transmits forces between the facial muscles and the skin. Progressive tissue laxity and changes in the properties of supporting structures contribute to the loss of facial contour.
- Craniofacial bone remodeling. With age, the dimensions and projection of the mandible, maxilla, and orbits change. Reduced bone support can leave a greater excess of soft tissue relative to the surface area of the skeleton.
- Individual predispositions. Genes, skin thickness, mandibular shape, chin projection, fat distribution, and natural facial asymmetry all play a role.
The process can be accelerated by ultraviolet radiation, tobacco smoking, and significant fluctuations in body weight. Rapid weight loss does not always reduce jowls. Loss of volume in the midface can actually reveal skin laxity and worsen tissue support. Chronological age alone also does not determine the severity of the problem.
Facial jowls - do home remedies work
Home methods can improve the condition of the skin surface, but they are not able to permanently reposition sagging fat compartments, shorten stretched fibrous connections, or alter the structure of the mandible. A systematic review of studies on facial exercises, massage, and myofunctional therapy indicates that the observed benefits are localized, and the quality of evidence remains insufficient to confirm an effective facelift.
Realistically assessed home measures include:
- daily broad-spectrum photoprotection, which limits further photoaging;
- the use of retinoids or retinol, if well tolerated, to support epidermal and dermal remodeling;
- moisturizing care that temporarily improves smoothness and epidermal barrier properties;
- not smoking, weight stabilization, and proper nutrition;
- gentle massage, which may transiently reduce swelling, but does not eliminate the anatomical cause of jowls.
Intense kneading, uncontrolled energy devices, strong lifting tapes, and self-injections can lead to irritation or tissue damage. "Face yoga" should not be presented as the equivalent of a medical procedure. A lifting cream may increase hydration and temporarily improve skin surface tension, but it does not act on deep fat compartments or the SMAS system.
Facial jowls - which treatment helps
There is no single best treatment for everyone. The method is selected based on the dominant cause, the severity of laxity, the amount of fat, the anatomy of the mandible, and the expected duration of the results.
At Ambasada Urody Clinic & Spa, the following groups of procedures are used, among others:
- Microneedle radiofrequency induces controlled micro-injuries and heating of the dermis. It stimulates collagen remodeling, which can improve skin density and tension in cases of mild to moderate laxity. However, it does not replace the mechanical lifting of significantly sagging tissues.
- Lifting threads, including APTOS and barbed threads, are used for the mechanical repositioning of selected tissues. The best results are usually achieved with mild to moderate sagging and preserved skin quality. Possible side effects include swelling, bruising, irregularities, palpability of the threads, infection, and asymmetry. The effect is less predictable and less durable than surgery.
- Volumetry with hyaluronic acid or calcium hydroxyapatite can enhance chin projection and the jawline or restore support in other parts of the face. The product should not be injected directly into every visible jowl, as an unjustified increase in volume can widen the lower face.
- Tissue stimulators serve primarily to improve skin quality and density. They can be part of a multi-stage therapy, but on their own they do not always provide significant lifting of heavy tissues.
- Poly-L-lactic acid (PLLA) stimulates fibroblasts to produce collagen, gradually improving skin density and tissue support. It can reduce the visibility of minor jowls associated with volume loss and laxity, but it does not remove fat or lift significantly sagging tissues. Treatment requires precise qualification, proper product dilution, and the appropriate level of administration. Improper administration may excessively widen the lower face.
- Injection lipolysis can be considered only when local excess fat is a significant component. In cases of predominant laxity, volume reduction may worsen the problem.
- Thermal and ultrasound technologies can cause controlled heating of specific tissue layers and gradual collagen remodeling. Effectiveness depends on proper qualification, device parameters, and the severity of changes.
In cases of advanced tissue sagging, a surgical lower facelift, sometimes combined with a neck lift, remains the most predictable method. Minimally invasive procedures are not an equivalent substitute.
Qualification should be performed by a physician with knowledge of facial anatomy and potential complications. It is especially important to avoid excessive fat reduction and accidental volume addition in the wrong layer. An optimal plan often combines improving skin quality, restoring support, and moderate tissue lifting, while maintaining natural facial proportions.

