Post-laser hyperpigmentation
back to main page
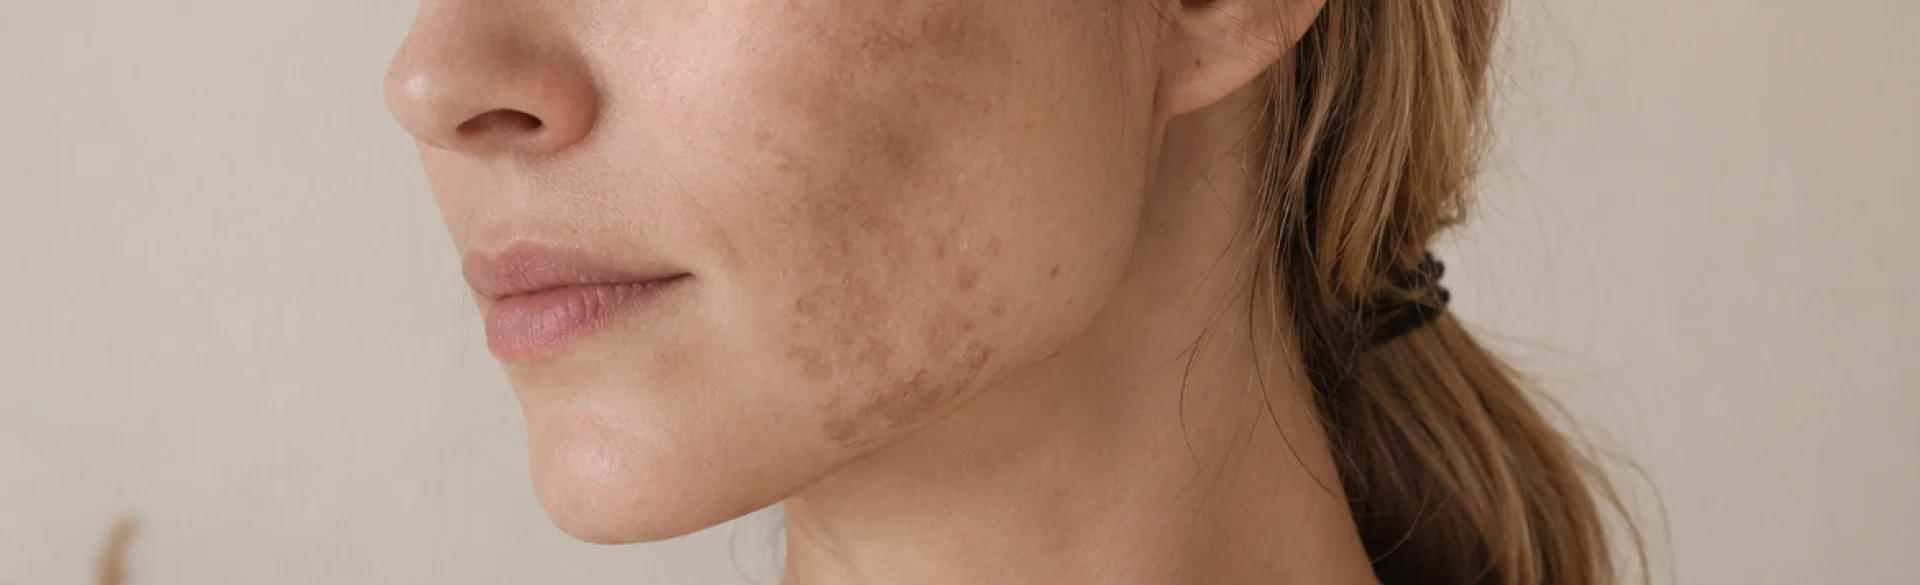
Post-laser hyperpigmentation refers to skin color changes that appear after procedures using light or thermal energy, including ablative, non-ablative, fractional, vascular, and pigment lasers. Most commonly, they take the form of post-inflammatory hyperpigmentation, referred to by the abbreviation PIH (post-inflammatory hyperpigmentation). They develop as a result of the temporary stimulation of melanocytes by inflammation caused by controlled skin damage. The lesion can be light brown, brown, or grayish-blue, depending on the depth of melanin accumulation. However, not every darkening of the skin immediately after the procedure signifies a complication. In the case of laser removal of pigmented lesions, temporary darkening of the treated spot may be an expected consequence of energy absorption by melanin. Persistent or worsening hyperpigmentation, on the other hand, requires evaluation by a specialist.
Hyperpigmentation after laser - why it occurs
The action of a laser is based on the selective delivery of energy to a specific chromophore, which is a light-absorbing molecule. The chromophore can be melanin, hemoglobin, or water. Even a properly performed procedure induces a controlled inflammatory response, which is part of the skin remodeling and healing process.
Damaged keratinocytes and immune system cells release cytokines, chemokines, prostaglandins, leukotrienes, and other inflammatory mediators. These substances can stimulate melanocytes to:
- increase tyrosinase activity, a key enzyme in melanin synthesis,
- produce more melanosomes, which are pigment-containing organelles,
- enhance the transfer of melanosomes to keratinocytes,
- increase the production and uneven distribution of melanin.
If the inflammation remains confined to the epidermis, epidermal hyperpigmentation usually develops, taking on a light brown to dark brown color. Deeper damage to the basement membrane can lead to so-called pigmentary incontinence: melanin penetrates into the dermis and is engulfed by macrophages, referred to in this context as melanophages. This results in dermal hyperpigmentation, often gray, blue-gray, or brownish-gray, which resolves much more slowly.
The risk increases when the amount of energy, pulse density, pulse duration, or number of passes causes excessive tissue heating. Insufficient cooling, pulse overlap, and too short an interval between subsequent procedures are also significant. Hyperpigmentation can be further exacerbated by ultraviolet radiation, visible light, irritating cosmetics, mechanical removal of scabs, infection, or prolonged healing.
Discoloration after laser - who is at risk
Post-inflammatory hyperpigmentation can occur in individuals of any skin color, but it is usually more pronounced and persistent with higher melanocyte activity. Patients with Fitzpatrick skin phototypes III-VI require special caution. However, the phototype alone does not allow for an accurate prediction of the risk, and study results regarding its independent impact after CO₂ laser treatment are not completely conclusive.
The most important risk factors include:
- previous hyperpigmentation after acne, injuries, burns, or other procedures,
- melasma, also known as chloasma, and a tendency to recurrent pigmentation disorders,
- a fresh tan and recent exposure to UV radiation,
- intense sun exposure during the healing period,
- active dermatitis, acne, atopic dermatitis, or irritation of the treatment area,
- overly aggressive device parameters in relation to the phototype and indication,
- ablative treatments, high density of micro-injuries, or multiple passes over the same area,
- slow healing, secondary infection, prolonged erythema, or damaging scabs,
- the use of retinoids, acids, mechanical peels, or irritating cosmetics during the recovery period,
- certain medications and photosensitizing substances.
The risk also depends on the wavelength. Shorter wavelengths are more strongly absorbed by epidermal melanin, which is why treating darker phototypes requires particularly careful selection of parameters. In addition, the type of procedure is important: a fractional CO₂ laser causes a different degree of damage and inflammation than a non-ablative laser, a vascular laser, or a device designed for selective pigment removal.
Before the procedure, the phototype, current tan, previous reactions to procedures, medications taken, and the presence of skin diseases should be assessed. In cases of increased risk, performing a laser test spot on a small area and observing the reaction for an adequately long time may be helpful.
Discoloration after laser - after what time does it appear
The timing of the appearance of the lesion depends on its mechanism. Immediate darkening or darkening within a few hours of the treated spot may indicate an expected reaction of the pigment to laser energy. After laser removal of discoloration, the lesion often darkens first and then undergoes superficial exfoliation. Such a presentation should not be automatically equated with PIH.
Typical post-inflammatory hyperpigmentation usually becomes visible after the initial erythema, swelling, and peeling subside:
- in the first few days, redness and swelling may dominate,
- after a few days to a few weeks, brown darkening may appear,
- in the subsequent weeks, the color may temporarily intensify, especially after exposure to UV or visible light,
- the hyperpigmentation may persist for many months.
Delayed appearance is due to the fact that the synthesis, transport, and visible accumulation of melanin require time. Some lesions are noticed only when the post-treatment erythema, which previously masked the difference in color, disappears.
Extensive darkening, blisters, worsening pain, oozing, honey-yellow crusts, a marked exacerbation of erythema, or systemic symptoms are not typical features of isolated PIH. They may indicate a burn, infection, or impaired healing and require urgent consultation. Persistent erythema must also be distinguished from hyperpigmentation, as it is a vascular lesion and not the result of excess melanin.
Discoloration after laser - will it go away on its own
Many epidermal post-inflammatory hyperpigmentations gradually lighten without treatment, as melanin is removed by the physiological renewal of the epidermis. However, the process usually takes months, not days. Epidermal PIH can persist for about 6-12 months, while pigment present in the dermis can be visible for several years. The rate of improvement depends on the depth of the pigment, the intensity of inflammation, phototype, sun protection, and re-irritation of the skin.
The diagnosis must be confirmed before starting therapy. The doctor may use a dermatoscope or a Wood's lamp, although these methods do not always precisely determine the depth of the pigment. PIH must also be distinguished from a recurrence of the primary hyperpigmentation, melasma, post-inflammatory erythema, hypopigmentation, scarring, and certain melanocytic lesions.
The basis of management is photoprotection and resolving inflammation. After complete healing, the doctor may consider preparations that inhibit melanogenesis, including azelaic acid, retinoids, or hydroquinone, if available and appropriate for the patient. Improperly selected exfoliating treatment can sustain inflammation and paradoxically deepen pigmentation.
The current offer of Ambasada Urody includes hyperpigmentation reduction procedures that can only be considered after assessing the cause and depth of the lesion:
- Cosmelan and Dermamelan: multi-stage depigmentation treatments that inhibit the melanin production process; particularly associated with melasma, but qualification for PIH treatment requires individual evaluation.
- Medical peels with depigmenting agents: can accelerate the reduction of epidermal pigment, but overly intensive exfoliation itself can trigger further PIH.
- Alma Dye VL PRO laser hyperpigmentation removal: utilizes light absorbed by melanin and is primarily intended for specific pigmented lesions. In hyperpigmentation caused by a previous laser, the procedure should be approached with caution, as light-based devices can both reduce and worsen PIH.
- Fractional laser: may be considered in selected, resistant lesions and with coexisting skin structure abnormalities, but it is not a routine first-line treatment for fresh PIH.
- Intraceuticals: oxygen infusion with moisturizing and skin care supporting effects; it can complement regeneration, but does not replace depigmentation treatment.
- HydraFacial: a cleansing, exfoliating, and conditioning procedure whose intensity must be tailored to the condition of the epidermal barrier. It should not be performed on freshly damaged skin.
- LED therapy with red or yellow light: can support calming inflammation and regeneration. It does not directly remove deeply located melanin.
The choice of procedure should be based on diagnosis, not solely on the color of the spot. Systematic reviews indicate that laser and energy-based devices can provide partial improvement in PIH, but in some patients, they cause worsening. For this reason, they are usually a subsequent line of treatment after photoprotection and topical therapy.
Hyperpigmentation after laser - how to avoid it
Not every discoloration can be prevented, but proper qualification, treatment parameters, and post-treatment care significantly reduce the risk.
Before the procedure:
- avoid tanning and do not perform the procedure on freshly tanned skin,
- inform the specialist about melasma, prior PIH, skin conditions, and all medications,
- stabilize active acne, eczema, infection, or other sources of inflammation,
- discontinue irritating substances only as recommended by the practitioner,
- perform a laser test patch in selected cases,
- start regular photoprotection even before the procedure.
After the procedure, the following are crucial:
- using a broad-spectrum protection product, preferably SPF 50+, in the amount recommended by the manufacturer,
- reapplying during exposure and using clothing, a hat, and shade,
- considering a tinted product with iron oxides, especially for melasma and darker phototypes, as visible light can also enhance melanogenesis,
- gentle cleansing and rebuilding the epidermal barrier with emollients,
- not scratching scabs and not performing self-administered peels,
- avoiding retinoids, acids, cleansing brushes, cosmetic alcohol, and fragrances until healed,
- limiting skin overheating and intense exercise for the period indicated by the specialist,
- prompt consultation in case of prolonged erythema, blisters, pain, or symptoms of infection.
Laser parameters should be tailored to the phototype, type of lesion, and depth of the chromophore. Safety is increased by adequate cooling, limiting pulse overlap, appropriate wavelength, cautious energy density, and sufficiently long intervals between sessions. Pharmacological prophylaxis, including the use of topical corticosteroids or tranexamic acid, has been the subject of clinical trials, but should not be carried out independently. It requires an assessment of indications and contraindications by a physician, as the benefits depend on the type of procedure, and the treatment can cause adverse effects.

